Running a Pregnancy Programme? 12 Things to Get Right With Your Health Data
A practical guide for maternity services, pregnancy and femtech apps, insurers and employers, and public health programmes on the data decisions that shape care from the first antenatal visit to the year after birth.

Pregnancy is one of the most data-rich periods in a woman's life, and one of the most consequential. About 260,000 women died during and following pregnancy and childbirth in 2023, around 92% of them in low- and lower-middle-income countries, and most of those deaths were preventable.1, 2 Around 1.9 million babies were stillborn in 2023,3 and an estimated 13.4 million were born preterm in 2020.4
Many of the risks behind these numbers can be seen early, in a blood pressure reading, a glucose test, a scan or a change in how a woman feels. Whether anyone acts on them depends on the data being in the right place, read against the right week of pregnancy, and still connected when she moves between a clinic, a hospital, an app and home.
We wrote this guide for four groups of readers. If you run a clinic or maternity service, it covers how to keep a woman's record coherent across visits, providers and the months after birth. If you build a pregnancy or femtech app, it sets out the data decisions to get right before you scale. If you are an insurer or employer offering maternity support, it explains what good programme data looks like. If you lead a public health programme or non-governmental organisation, it covers what your data needs in order to be compared and acted on. The twelve points apply to all four, and where the emphasis differs, we say so.
Where pregnancy data actually lives
A woman in her first pregnancy may book with a private obstetrician, have her dating scan at an imaging centre, have her blood tests at a laboratory chain, carry an antenatal card or handbook to every appointment, check her blood pressure at home, and track symptoms in an app. She may give birth in a hospital that has never seen most of this, and her baby's record begins there, often with little link back to hers.
Each source holds part of the story. The value for women, clinicians and programmes comes from bringing them together, against the right week of pregnancy, and keeping them connected after birth.
The twelve points below are grouped into four themes: getting the clinical picture right, making the data usable, connecting the longer story, and building for trust and scale. After them, we set out what to capture at each stage, from before conception to the year after birth.
Get the clinical picture right
1. Date the pregnancy correctly, and keep every record in step
Almost everything in pregnancy is read against gestational age: whether a scan measurement is normal, when a screening test is due, whether a birth is preterm, and what a blood result means. The World Health Organization (WHO) recommends one ultrasound scan before 24 weeks of gestation, partly to estimate gestational age accurately.5 The American College of Obstetricians and Gynecologists (ACOG) states that ultrasound measurement in the first trimester, up to and including 13 weeks and 6 days, is the most accurate way to establish or confirm gestational age.6
ACOG also sets out when a due date based on the last menstrual period should be changed after an ultrasound: for example, when the two differ by more than 7 days between 9 weeks and 15 weeks and 6 days, with wider margins later in pregnancy. Once set, the due date should be documented clearly, and later changes kept for rare circumstances, discussed with the woman and documented.6 In practice, data systems often hold several due dates at once, from the app, the clinic and the scan, and results end up read against different weeks.
What good looks like: one documented due date with the method used and the date it was set, gestational age recorded with every observation, and a clear audit trail if the date is ever revised, so that earlier observations are recalculated rather than left out of step.
Matters most to: Clinics and maternity services, Digital health teams
2. Record obstetric history and risk factors as structured data
A woman's history shapes the care she needs in this pregnancy: how many times she has been pregnant and given birth, how earlier pregnancies ended, whether she had high blood pressure, gestational diabetes, a preterm birth or a caesarean section before, and whether she has conditions such as diabetes, hypertension, thyroid disease or epilepsy. Whether this is a twin or other multiple pregnancy changes almost everything that follows.
This information is often captured once, at booking, in free text or on paper, and never carried forward in a way systems can use. That makes it hard to target extra monitoring to the women who need it, or for a programme to show whether higher-risk women were identified early.
What good looks like: obstetric history, pre-existing conditions and pregnancy-specific risk factors recorded as structured, dated fields that travel with the record and are reviewed as the pregnancy progresses.
Matters most to: Clinics and maternity services, Insurers and employers, Public health and NGOs
3. Use pregnancy-specific reference ranges
Pregnancy changes what "normal" looks like for many laboratory tests, so general adult ranges can mislead. The WHO's 2024 guideline on haemoglobin cut-offs defines anaemia in pregnancy as a haemoglobin below 110 g/L in the first and third trimesters and below 105 g/L in the second.7 For thyroid function, the American Thyroid Association recommends population-based, trimester-specific reference ranges for thyroid-stimulating hormone (TSH), with a fallback upper limit of about 4.0 mU/L when those are not available.8
Laboratory reports often print a general adult range beside a pregnant woman's result. A tool that flags against that range, or fails to flag because the printed range is wider, will send the wrong message.
What good looks like: results interpreted against pregnancy-specific and, where relevant, trimester-specific ranges, with the original laboratory range kept for reference and the gestational age at the time of testing stored alongside.
Matters most to: Clinics and maternity services, Digital health teams
Make the data usable
4. Link mother and baby records
Pregnancy is the one area of healthcare where one timeline holds two patients, or more in a multiple pregnancy. Before birth, scans and tests of the baby sit in the mother's record. At birth, the baby gets a record of its own, usually in a different system, and the connection is often lost. Yet much of what matters for the baby, such as the mother's gestational diabetes, blood group, infections or medicines, is in her record, and much of what matters for her recovery depends on how the baby is doing.
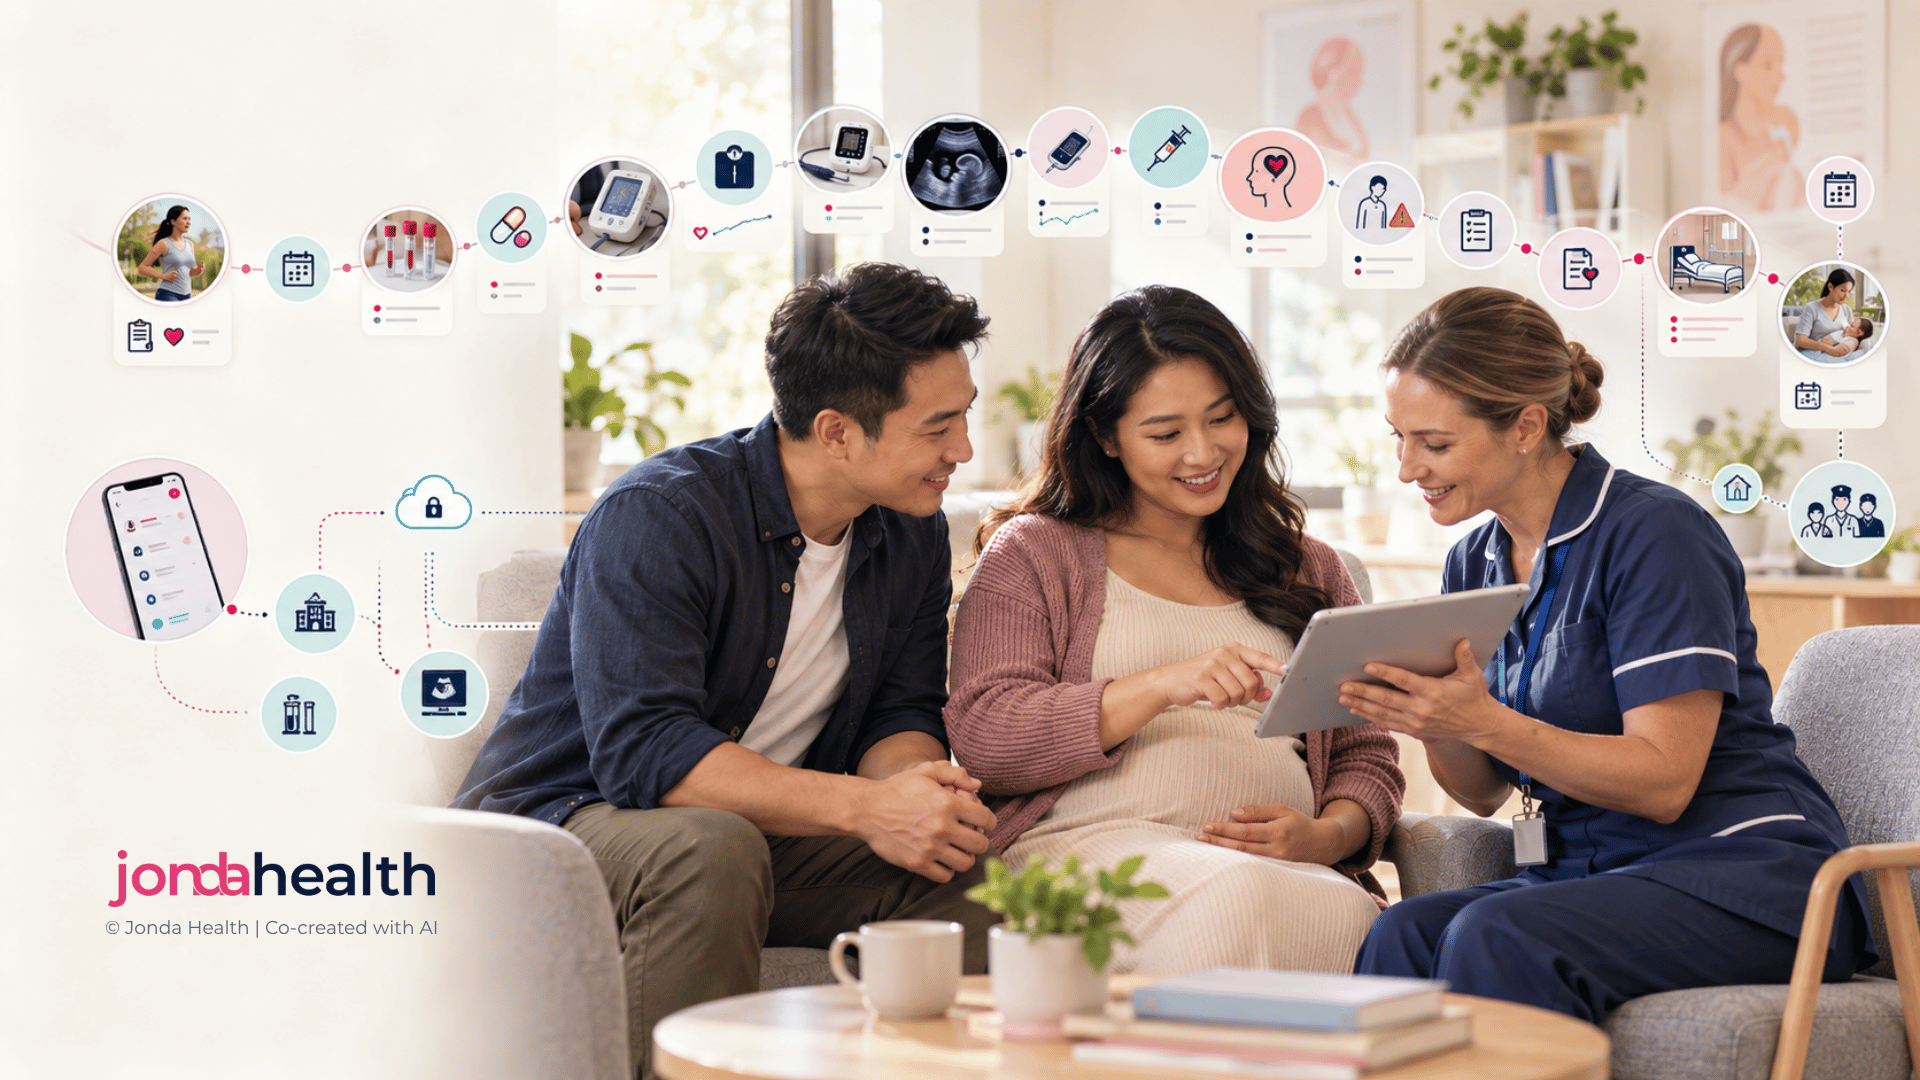
An illustrative timeline, not to scale. The mother's record carries on through the year after birth, while the baby's record begins at birth and should stay linked to hers.
What good looks like: each baby given its own identifier and record at birth, explicitly linked to the mother's record and pregnancy, with the relevant parts of her history available to the baby's clinicians and consent managed for each person separately.
Matters most to: Clinics and maternity services, Public health and NGOs, Digital health teams
5. Turn scans and screening results into data
Much of the clinical story of a pregnancy lives in documents: dating and anomaly scan reports, growth scans, screening results and letters from specialists. They arrive as PDFs, printouts and phone photos, in different layouts and sometimes different languages. The findings that matter, such as the estimated due date, the number of babies, placental position or a recommendation for follow-up, need to be identified, structured and linked to the right gestational age.
Screening tests need the same care, because the criteria differ. For gestational diabetes, the WHO's 2013 criteria for a 75 g oral glucose tolerance test (OGTT) are a fasting glucose of 5.1 to 6.9 mmol/L, a 1-hour value of 10.0 mmol/L or above, or a 2-hour value of 8.5 to 11.0 mmol/L, with any one value enough for diagnosis.9 The National Institute for Health and Care Excellence (NICE) in the United Kingdom uses a fasting glucose of 5.6 mmol/L or above or a 2-hour value of 7.8 mmol/L or above,10 and the American Diabetes Association (ADA) also describes a two-step approach used in the United States.11 The same result can mean a diagnosis in one programme and not in another.
What good looks like: scan and screening findings extracted into structured fields with clinical review, stored with the gestational age and the criteria applied, and the original report kept alongside.
Matters most to: Clinics and maternity services, Digital health teams, Public health and NGOs
6. Structure medicines and supplements
Supplements are part of standard antenatal care. The WHO recommends daily oral iron and folic acid supplementation in pregnancy, with 30 to 60 mg of elemental iron and 400 µg (0.4 mg) of folic acid.5 Taken from before conception, folic acid reduces the risk of neural tube defects.12 Many women also take medicines for existing conditions that need to be reviewed, changed or continued in pregnancy, and some start new ones, such as treatment for high blood pressure or diabetes.
These records are often scattered across prescriptions from different doctors, over-the-counter purchases and products bought in other countries under different brand names.
What good looks like: each medicine and supplement recorded with its active ingredient, dose, route, start and stop dates and prescribing source, with the gestational age at each change and mapping to medical coding standards so brand and country differences do not fragment the history.
Matters most to: Clinics and maternity services, Digital health teams
Connect the longer story
7. Track blood pressure and glucose properly
High blood pressure and raised glucose are two of the most important things to monitor in pregnancy, and much of that monitoring now happens at home. The International Society for the Study of Hypertension in Pregnancy (ISSHP) defines hypertension in pregnancy as a systolic blood pressure of 140 mmHg or more and/or a diastolic of 90 mmHg or more, based on an average of at least two measurements, and severe hypertension as 160 mmHg or more systolic and/or 110 mmHg or more diastolic. Pre-eclampsia is defined as hypertension at or after 20 weeks with new-onset proteinuria, other maternal organ dysfunction or uteroplacental dysfunction.13
ISSHP recommends that blood pressure, in any setting, be measured with a device validated for use in pregnancy and pre-eclampsia.13 Many are not: a study of 54 home blood pressure devices sold in Australian pharmacies found only four were validated for pregnancy.14 Home glucose readings for gestational diabetes are often kept in handwritten logs or as photos of the meter screen.
What good looks like: each reading stored with its date, time, device and whether the device is validated for pregnancy, home readings turned into structured data rather than left as photos or notes, and clear thresholds that trigger review.
Matters most to: Clinics and maternity services, Digital health teams, Insurers and employers
8. Carry on after birth, through the first year
Many pregnancy programmes end at delivery, but the months after birth carry real risk. The WHO recommends at least four postnatal care contacts in the first six weeks: within 24 hours, at 48 to 72 hours, at 7 to 14 days and in week six.15 ACOG describes postpartum care as an ongoing process rather than a single visit, with contact within the first three weeks and a comprehensive visit no later than 12 weeks after birth.16 Deaths from pregnancy-related causes between 42 days and one year after the end of pregnancy are counted separately as late maternal deaths, which is one reason the whole first year matters.17
Mental health is a major part of this period. Worldwide, about 10% of pregnant women and 13% of women who have just given birth experience a mental disorder, primarily depression, rising to 15.6% and 19.8% in developing countries.18 ACOG recommends screening for depression and anxiety at the first prenatal visit, later in pregnancy and at postpartum visits,19 and the Edinburgh Postnatal Depression Scale (EPDS) is a widely used, validated 10-item tool.20
Gestational diabetes also needs follow-up. Women with gestational diabetes have almost ten times the risk of developing type 2 diabetes later.21 The ADA recommends a 75 g OGTT 4 to 12 weeks after birth using non-pregnancy criteria, then lifelong screening every one to three years.22 NICE recommends a fasting plasma glucose test 6 to 13 weeks after birth, then an annual HbA1c (glycated haemoglobin) test.10 This follow-up is easily lost when a woman's care passes from maternity services back to primary care.
What good looks like: a record that continues through the year after birth, with postnatal contacts, mood screening scores on a validated instrument, and follow-up tests after gestational diabetes or high blood pressure scheduled, tracked and handed over to the clinician who will see her next.
Matters most to: Clinics and maternity services, Insurers and employers, Digital health teams, Public health and NGOs
9. Follow women across providers and borders
Women often move between public and private care, change clinics during pregnancy, or return to their family's home town or home country to give birth. The WHO recommends that each pregnant woman carries her own case notes during pregnancy to improve continuity, quality of care and her experience.5 The Maternal and Child Health Handbook, which originated in Japan in the late 1940s, is now used in about 50 countries.23
Hand-held records are valuable precisely because they travel with the woman, but on their own they cannot be searched, analysed or shared with a system that was not there when they were written. In many programmes across Southeast Asia and Africa, the handbook is the most complete record that exists.
What good looks like: hand-held records and records from other providers or countries brought into a structured digital record, in any language, while the woman keeps her own copy, so that neither replaces the other.
Matters most to: Public health and NGOs, Clinics and maternity services
Build for trust and scale
10. Escalate warning signs, don't just log them
Some symptoms in pregnancy need urgent care. The WHO lists danger signs that mean a woman should go to a health facility immediately, day or night, including vaginal bleeding, convulsions, severe headache with blurred vision, fever with weakness, severe abdominal pain and fast or difficult breathing.24 The United States Centers for Disease Control and Prevention (CDC) also lists a baby's movements stopping or slowing during pregnancy among the urgent maternal warning signs.25
A symptom tracker that records "headache, severe" or "baby moving less" as another data point, to be reviewed at the next appointment, is working against the woman it is meant to support.
What good looks like: warning signs defined from a named guideline, each linked to a clear action written in plain language, local emergency contacts shown at the moment they are needed, and escalations recorded so the programme can check they worked.
Matters most to: Digital health teams, Clinics and maternity services, Insurers and employers
11. Protect the most sensitive data, and handle pregnancy loss with care
Pregnancy data is among the most sensitive information a person can share. It can reveal pregnancy intentions, fertility treatment, pregnancy loss and termination, and it falls within the special categories of health data protected under laws such as the General Data Protection Regulation (GDPR) and Singapore's Personal Data Protection Act (PDPA). In the United States, a federal rule adding privacy protections for reproductive health information under the Health Insurance Portability and Accountability Act (HIPAA) was published in 2024 and vacated nationwide by a court in June 2025,26 which leaves more of the responsibility with the organisations that hold the data.
Pregnancy loss is far more common than many products are designed for. About 15.3% of recognised pregnancies end in miscarriage, around 23 million a year worldwide.27 A study of 166 pregnancy apps found that 72% did not account for pregnancy loss at all.28 When a system cannot record a loss, it carries on as if the pregnancy continued, sending weekly milestones, baby-size comparisons, product suggestions and appointment reminders to someone who is grieving.
What good looks like: granular consent recorded with the data, pseudonymisation for any use beyond direct care, strict limits on sharing with employers, insurers and advertisers, and a loss pathway that has been designed and tested with people who have experienced it.
Matters most to: Digital health teams, Insurers and employers, Clinics and maternity services
12. Use definitions that compare
Programmes working across countries quickly find that the same words mean different things. For international comparison, the WHO defines stillbirth as a baby born with no signs of life at 28 weeks of gestation or more.29 In the International Classification of Diseases, 11th revision (ICD-11), the perinatal period begins at 22 completed weeks.30 National definitions differ again: 20 weeks or more in the United States (CDC),31 20 completed weeks or 400 g or more in Australia,32 and after 24 completed weeks in the United Kingdom.33 Preterm birth means before 37 completed weeks,4 and a maternal death is one during pregnancy or within 42 days of its end.17
The same loss can be counted as a stillbirth in one country and not in another. Australia also uses a birthweight of 400 g or more.32
If a programme's data does not record the gestational age and birthweight behind each outcome, it cannot be recalculated for a different definition, and results from different countries cannot be compared or combined.
What good looks like: outcomes stored with the underlying facts (gestational age, birthweight, signs of life, timing after birth), so they can be classified under any definition, with the definition used for each report recorded explicitly.
Matters most to: Public health and NGOs, Insurers and employers, Clinics and maternity services
What to capture, stage by stage
The twelve points apply across pregnancy, but each stage brings its own data. This summary shows the core items most programmes will need, from before conception to the year after birth.
Where to start, depending on who you are
You do not need to solve all twelve at once. The right starting point depends on what your data needs to do.
How a programme team can use this guide
Teams tend to get the most from these twelve points when they use them as a working tool rather than a reading list.
If you would like support with this, the Health Data Foundations work within Jonda Health Services takes a programme through exactly these questions, from what data you hold and where it sits to what it needs before it can support analytics, AI or evidence generation. Our Experience Design work helps teams design journeys women can trust, including the moments that are hardest to get right, and our insight and analytics work helps turn a harmonised dataset into measures and benchmarks your stakeholders can use.
How Jonda Health can help
Much of what sits between a pregnancy programme and a record that supports women well is data work. It means bringing together antenatal notes, scan reports, laboratory results, hand-held records and home readings, making them usable across formats and languages, cleaning them, resolving the many ways the same thing gets captured, reviewing them clinically and mapping them to medical coding standards. This is the work we do every day.
JondaX, our health data transformation engine, turns laboratory reports, clinical documents, medical device readings and wearable data into structured, harmonised data through a single API, with other clinical data types configured to your needs. Its medical device scan turns a photo of a blood pressure monitor or glucose meter into structured data, which suits home monitoring in pregnancy. Every dataset goes through human-in-the-loop review by clinically trained reviewers, so that the burden of checking does not fall on your team. JondaX supports more than ten languages, can be deployed and processed within your country where required, supports pseudonymisation of data for secondary use, and works with your own ontology and code sets. Jonda Health is ISO 27001 certified, and our platform is designed to comply with HIPAA, GDPR and PDPA.
Frequently asked questions
What data should a pregnancy programme collect?
At a minimum: a documented due date and how it was set, gestational age at every observation, obstetric history and risk factors, results with pregnancy-specific reference ranges, scan and screening findings as structured data, medicines and supplements, blood pressure and glucose readings, warning signs with clear escalation, and follow-up through the year after birth, with the baby's record linked to the mother's.
Why does gestational age matter so much in pregnancy data?
Almost every result, scan finding, screening test and risk in pregnancy is interpreted against gestational age.6 If the due date is wrong, or changes without every observation being updated, results are read against the wrong week and trends stop making sense.
How should a pregnancy app or programme handle pregnancy loss?
Make it easy and gentle to record a loss, and make that one change stop every related reminder, milestone, content feed and marketing message across all systems. Offer appropriate support, keep the history accurate for future care, and never require the person to explain the loss more than once.
Which criteria are used to diagnose gestational diabetes?
Criteria differ. The WHO's 2013 criteria use a 75 g oral glucose tolerance test with any one of a fasting value of 5.1 to 6.9 mmol/L, a 1-hour value of 10.0 mmol/L or above, or a 2-hour value of 8.5 to 11.0 mmol/L.9 NICE uses a fasting value of 5.6 mmol/L or above or a 2-hour value of 7.8 mmol/L or above,10 and a two-step approach is also used in the United States.11 Programmes should record which criteria were applied.
What follow-up is needed after gestational diabetes?
The American Diabetes Association recommends testing 4 to 12 weeks after birth with a 75 g oral glucose tolerance test and non-pregnancy criteria, then lifelong screening every one to three years.22 NICE recommends a fasting plasma glucose test 6 to 13 weeks after birth, then an annual HbA1c test.10
References
- World Health Organization. Maternal mortality, fact sheet, 7 April 2025.
- World Health Organization, UNICEF, UNFPA, World Bank Group and UNDESA/Population Division. Trends in maternal mortality 2000 to 2023. 2025.
- UNICEF. Stillbirths, United Nations Inter-agency Group for Child Mortality Estimation data.
- World Health Organization. Preterm birth, fact sheet, 10 May 2023.
- World Health Organization. WHO recommendations on antenatal care for a positive pregnancy experience. 2016. Recommendations A.2.1, B.2.4, E.1 and E.7.
- American College of Obstetricians and Gynecologists. Committee Opinion No. 700: Methods for estimating the due date. Obstetrics & Gynecology. 2017;129(5):e150-e154.
- World Health Organization. Guideline on haemoglobin cutoffs to define anaemia in individuals and populations. 2024.
- Alexander EK, et al. 2017 Guidelines of the American Thyroid Association for the diagnosis and management of thyroid disease during pregnancy and the postpartum. Thyroid. 2017.
- World Health Organization. Diagnostic criteria and classification of hyperglycaemia first detected in pregnancy. 2013.
- National Institute for Health and Care Excellence. Diabetes in pregnancy: management from preconception to the postnatal period (NG3).
- American Diabetes Association. Standards of Care in Diabetes 2025, Section 2: Diagnosis and classification of diabetes. Diabetes Care. 2025;48(Suppl 1).
- United States Preventive Services Task Force. Folic acid for the prevention of neural tube defects: preventive medication. 2023.
- Magee LA, et al. The 2021 International Society for the Study of Hypertension in Pregnancy classification, diagnosis and management recommendations for international practice. Pregnancy Hypertension. 2022;27:148-169.
- Slater, Speer, Chapman, Picone. Validation status of home blood pressure devices sold in Australian pharmacies for use in pregnancy. Hypertension Research. 2025.
- World Health Organization. WHO recommendations on maternal and newborn care for a positive postnatal experience. 2022.
- American College of Obstetricians and Gynecologists. Committee Opinion No. 736: Optimizing postpartum care. 2018.
- World Health Organization. Maternal mortality ratio, indicator metadata, including definitions of maternal death and late maternal death.
- World Health Organization. Maternal mental health.
- American College of Obstetricians and Gynecologists. Clinical Practice Guideline No. 4: Screening and diagnosis of mental health conditions during pregnancy and postpartum. Obstetrics & Gynecology. 2023;141(6).
- Cox JL, Holden JM, Sagovsky R. Detection of postnatal depression: development of the 10-item Edinburgh Postnatal Depression Scale. British Journal of Psychiatry. 1987;150:782-786.
- Vounzoulaki E, et al. Progression to type 2 diabetes in women with a known history of gestational diabetes: systematic review and meta-analysis. BMJ. 2020;369:m1361.
- American Diabetes Association. Standards of Care in Diabetes 2025, Section 15: Management of diabetes in pregnancy. Diabetes Care. 2025;48(Suppl 1).
- Japan International Cooperation Agency. Maternal and Child Health Handbook. 2024. See also Baequni and Nakamura, Journal of International Health, 2012.
- World Health Organization. Pregnancy, childbirth, postpartum and newborn care: a guide for essential practice. 3rd edition, 2015.
- United States Centers for Disease Control and Prevention. Urgent maternal warning signs, HEAR HER campaign.
- Holland & Knight. HIPAA's reproductive health rule is vacated nationally. June 2025.
- Quenby S, et al. Miscarriage matters: the epidemiological, physical, psychological, and economic costs of early pregnancy loss. The Lancet. 2021;397:1658-1667.
- Andalibi N. Disruptive life events and pregnancy apps. New Media & Society. 23(3).
- World Health Organization. Stillbirth rate, indicator metadata.
- World Health Organization. Perinatal mortality rate, indicator metadata.
- United States Centers for Disease Control and Prevention. About stillbirth.
- Australian Institute of Health and Welfare. Stillbirths and neonatal deaths in Australia: definitions used in reporting.
- National Health Service. Stillbirth.
This guide is for teams designing and running pregnancy and maternity programmes, services and apps. It is not clinical advice for individuals. If you are pregnant and worried about a symptom, contact your midwife, doctor or local emergency services.