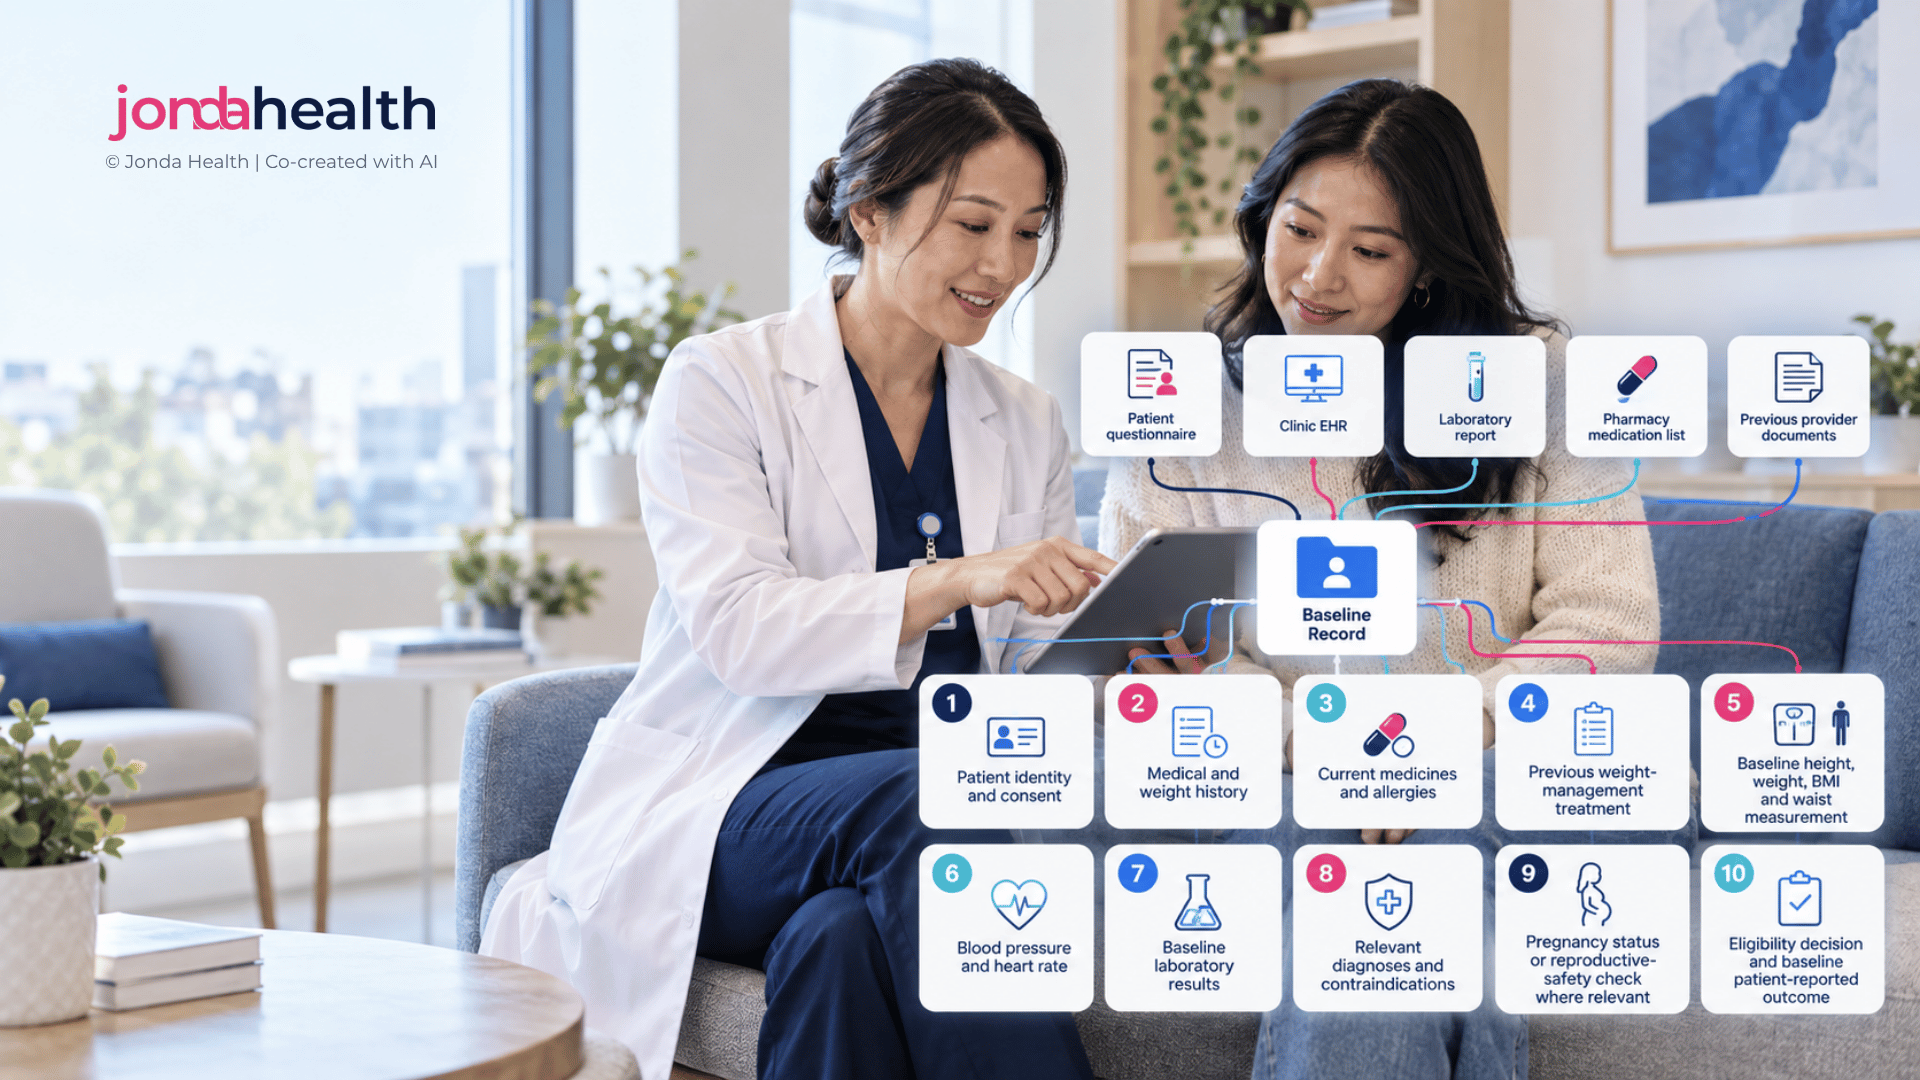
Before the First Dose: 10 Records Every GLP-1 Programme Needs on File
Every safety check, eligibility decision and outcome report in a GLP-1 programme depends on what was recorded before treatment started. This checklist sets out the ten records to have in place at baseline, and where they usually come from.
Suhina Singh
Founder & CEO, Jonda Health
October 23, 2026
·
10 min read
The baseline is the most valuable moment in a GLP-1 programme's data, and the easiest to rush. A new patient is keen to start, a clinician needs to make a prescribing decision, and the records that matter are scattered across laboratory PDFs, letters from other doctors, pharmacy histories and a patient questionnaire.
Whatever is missing on day one is very hard to recover later. You cannot measure a starting weight retrospectively, and a payer reviewing eligibility six months on will not accept "we think it was about 36". The ten records below are the ones that most often decide whether a programme can prescribe safely, prove eligibility and, later, show that it works.
This guide is about records and data, not clinical advice. Prescribing decisions rest with your clinicians and the product label that applies in your market. The label references below are to the US prescribing information.
The ten records at a glance
01Measured weight, height and waist
02Weight history and previous treatment
03Evidence for the conditions that make someone eligible
04Baseline blood tests, with their context
05The history that rules treatment out
06The history that changes monitoring
07A complete current medicines list
08Pregnancy plans and contraception
09A strength and function starting point
10Consent that covers how the data will be used
Most of a baseline arrives as documents. It only becomes a record once it is read, checked and stored as data.
1. Measured weight, height and waist
Body mass index (BMI) is calculated from weight and height, and it drives eligibility in almost every market. Record weight, height and waist circumference with a date, the place they were taken and the device used. Just as important, record whether each figure was measured by your team, taken from another provider's record, or reported by the patient.
MEASUREDTaken by our team, device recordedEXTERNALFrom another provider's record, source keptSELF-REPORTEDPatient's own figure, to be confirmed
Tip: A telehealth programme can accept a home scale reading at intake, as long as it is labelled as such and the patient sends a photo of the display. A source label costs nothing and saves arguments later.
2. Weight history and previous treatment
Many people arrive having already tried a weight management medicine, sometimes a GLP-1 from another provider, a pharmacy or an online service. That history changes how you interpret everything that follows. Someone who has already lost weight on another product will find a response target such as NICE's 5% at six months harder to reach, a point clinicians have raised about the guidance.1
It also matters for eligibility. The United States Medicare GLP-1 Bridge pilot judges BMI at the start of GLP-1 therapy, not on the day of the request. So a person who started at a BMI of 37 and now measures 34 can still qualify, as long as the prescriber can show where they started.2
Based on the example published in US coverage of the Medicare GLP-1 Bridge.2
Tip: Ask for the product, doses, dates and starting weight of any previous treatment, and request the dispensing or clinic record rather than relying on memory.
3. Evidence for the conditions that make someone eligible
Most coverage rules combine BMI with one or more weight-related conditions, and each payer asks for evidence, not a tick box. The conditions differ by market, so the evidence you keep should match the rule you are applying.
Payer or guideline
Examples of qualifying conditions
Evidence to keep
US Medicare GLP-1 Bridge
Prediabetes, chronic kidney disease stage 3a or higher, uncontrolled hypertension, heart failure with preserved ejection fraction3
The laboratory result, blood pressure readings or specialist letter behind each diagnosis
England, NICE TA875
At least one weight-related comorbidity, with BMI criteria4
Diagnosis records and referral criteria met
Australia, proposed PBS listing
Documented prior heart attack or stroke, or symptomatic peripheral arterial disease5
Hospital discharge summary or cardiology letter
Employer and insurer programmes
Set by the plan; often similar combinations
Whatever the plan's criteria name, in a form an auditor can check
Pitfall: The evidence for a qualifying condition is often a discharge summary or letter written years ago, in another language or another system. If it is not found and structured at intake, eligibility rests on a note that says "history of stroke".
4. Baseline blood tests, with their context
Baseline blood tests set the starting point for the outcomes payers value most, and help clinicians spot reasons for caution. Patients often bring recent results from another laboratory, which is useful as long as each value keeps the context that makes it comparable later.
Common baseline test
Why it matters later
Glycated haemoglobin (HbA1c) and fasting glucose
Shows change in glucose status, a key outcome for payers
Lipids
Cardiovascular risk outcomes
Kidney function (creatinine, estimated glomerular filtration rate)
Eligibility in some markets, and safety monitoring
Liver function
Starting point for liver-related outcomes
5. The history that rules treatment out
Both semaglutide (Wegovy) and tirzepatide (Zepbound) carry a boxed warning about thyroid C-cell tumours, and are contraindicated in people with a personal or family history of medullary thyroid carcinoma (MTC) or multiple endocrine neoplasia syndrome type 2 (MEN 2), and in people with a known serious hypersensitivity to the medicine.6, 7
A family history is easy to miss in a short telehealth intake. Ask the question explicitly, record the answer as a structured field (yes, no or unknown), and keep any supporting letter.
Drawn from the warnings and contraindications in the US prescribing information for Wegovy and Zepbound.6, 7
6. The history that changes monitoring
Other conditions do not rule treatment out, but the labels ask prescribers to watch for them. They include acute pancreatitis, gallbladder disease, acute kidney injury (particularly with dehydration from gastrointestinal side effects), and, in people with diabetes, progression of diabetic retinopathy.6, 7 Knowing this history at baseline is what allows a programme to set up the right follow-up from the start.
Tip: Hospital discharge summaries are the richest source for this history. Ask patients for any they have, and make sure the diagnoses inside them are captured as data, not left as an attachment.
7. A complete current medicines list
Two medicine groups come up repeatedly in the labels. The risk of low blood sugar rises when a GLP-1 is used with insulin or sulfonylureas, and the doses of those medicines may need to be reduced.6, 7 For tirzepatide, the label advises people using oral hormonal contraceptives to switch to a non-oral method, or add a barrier method, for four weeks after starting and for four weeks after each dose increase.7
From the US prescribing information.6, 7 Check the label that applies in your market.
Pitfall: Patients often leave out medicines prescribed by another doctor, supplements and products bought online. A pharmacy dispensing record is a useful cross-check where you can get one.
8. Pregnancy plans and contraception
Weight loss medicines are not used in pregnancy, and the Wegovy label advises stopping at least two months before a planned pregnancy because of the medicine's long half-life.6 For people who could become pregnant, record current contraception and any plans for pregnancy at baseline, and revisit them at each review.
From the US Wegovy prescribing information.6
9. A strength and function starting point
If your programme will ever be asked about muscle loss, and most will, you need to know where each person started. A joint advisory from four obesity and nutrition societies recommends assessing muscle strength and function at the start of GLP-1 therapy, for example with a sit-to-stand test, and considering a measure of muscle mass where available.8 A grip strength reading and a timed chair-stand test take only a few minutes and work in a clinic, a pharmacy or over video.
Tip: Our guide to tracking muscle on GLP-1 treatment covers which measures to use, how to standardise them and which thresholds apply in Asian and European populations.
10. Consent that covers how the data will be used
Baseline records are health data, which most privacy laws protect as a special category. Consent at intake should be clear about each way the data will be used, because a GLP-1 programme often serves more than one party: the patient's care, the employer or insurer paying for the programme, and sometimes research or service improvement.
Pitfall: An employer-sponsored programme that sends identifiable outcomes back to the employer can damage trust quickly. Decide at the start what the sponsor sees, and say so in the consent.
How Jonda Health can help
Most of a baseline arrives as documents: laboratory reports in different formats and languages, discharge summaries, specialist letters and photos of home readings. Turning them into a checked, structured record before the first prescription is where programmes lose the most time, and it is the work we do every day.
JondaX
Turn intake documents into a baseline
One API for laboratory reports, clinical documents, discharge summaries and photographed device readings, in 10+ languages.
Keeps units, dates, laboratory and reference ranges with every value, and maps results to medical coding standards or your own code sets.
Clinically trained reviewers check flagged results, with 99% field-level accuracy after expert review.
ISO 27001 certified, designed to comply with HIPAA, GDPR and PDPA, and deployable in country.
Jonda Health Services
Design the intake around it
Intake journeys that ask for the right documents and questions at the right time.
Baseline data models aligned to the eligibility rules of each payer you serve.
Consent, pseudonymisation and data flows that meet local rules.
Integration planning into your platform, electronic health record or clinic system.
See it on your own records. Send us a sample of real intake documents (up to 20 pages) and we will run them through JondaX free of charge, so you can see the structured baseline next to the originals. If you would rather talk it through first, book a free 30-minute data readiness conversation.
Kahal H, Walton C. A critique of semaglutide (Wegovy) for obesity management: NICE technology appraisal TA875. British Journal of Diabetes. bjd-abcd.com
NPR via St. Louis Public Radio. A new Medicare option for weight-loss drugs is coming. Here's what to know. 2026. stlpr.org
UnitedHealthcare. Medicare GLP-1 Bridge program: what you need to know. 2026. uhcprovider.com
National Institute for Health and Care Excellence. Semaglutide for managing overweight and obesity (TA875). 2023. nice.org.uk/guidance/ta875
Pharmaceutical Benefits Scheme. Medicine status: semaglutide (Wegovy), information current as at 1 October 2026. pbs.gov.au/medicinestatus/document/1650
Novo Nordisk. Wegovy (semaglutide) injection, US prescribing information. accessdata.fda.gov/drugsatfda_docs/label/2024/215256s011lbl.pdf
Eli Lilly. Zepbound (tirzepatide) injection, US prescribing information. pi.lilly.com/us/zepbound-uspi.pdf
Nutritional priorities to support GLP-1 therapy for obesity: a joint advisory from the American College of Lifestyle Medicine, the American Society for Nutrition, the Obesity Medicine Association, and The Obesity Society. 2025. pmc.ncbi.nlm.nih.gov/articles/PMC12304835