For patient organisations, clinician networks, pharma medical affairs teams and government agencies who want a registry that people keep contributing to and that can stand behind real decisions.

Most disease registries do not fail at launch. The launch is usually the easy part: there is funding, enthusiasm and a group of committed sites. The difficulty tends to arrive in the second and third years, when entering data becomes one more task for busy clinical teams, when years of patient history are still sitting in PDFs and scanned letters, and when the people who want to use the data are not yet confident enough in it to publish, plan services or support a regulatory submission.
A patient registry is an organised system that collects uniform data over time on people diagnosed with a particular disease or condition.2 The words that matter in that definition are "uniform" and "over time". Both are harder to achieve than they look, and both depend far more on the data layer than on the software chosen to hold it.
This guide sets out 12 things we see make the difference between a registry that quietly stalls and one that keeps becoming more useful. It draws on published good practice from the United States Agency for Healthcare Research and Quality (AHRQ), the European Medicines Agency (EMA), the United States Food and Drug Administration (FDA) and the European Platform on Rare Disease Registration, alongside our own work turning messy clinical data into structured, standardised information.
One note before we begin. The four groups this guide is written for often want different things from the same registry. A patient organisation may want to understand the lived course of a condition and advocate for services. A clinician network may want to benchmark care. A medical affairs team may want natural history data or post-approval evidence. A government agency may want to plan resources and monitor outcomes. None of these goals is wrong, but a registry that tries to serve all of them without agreeing priorities usually serves none of them well. That tension runs through several of the points below.
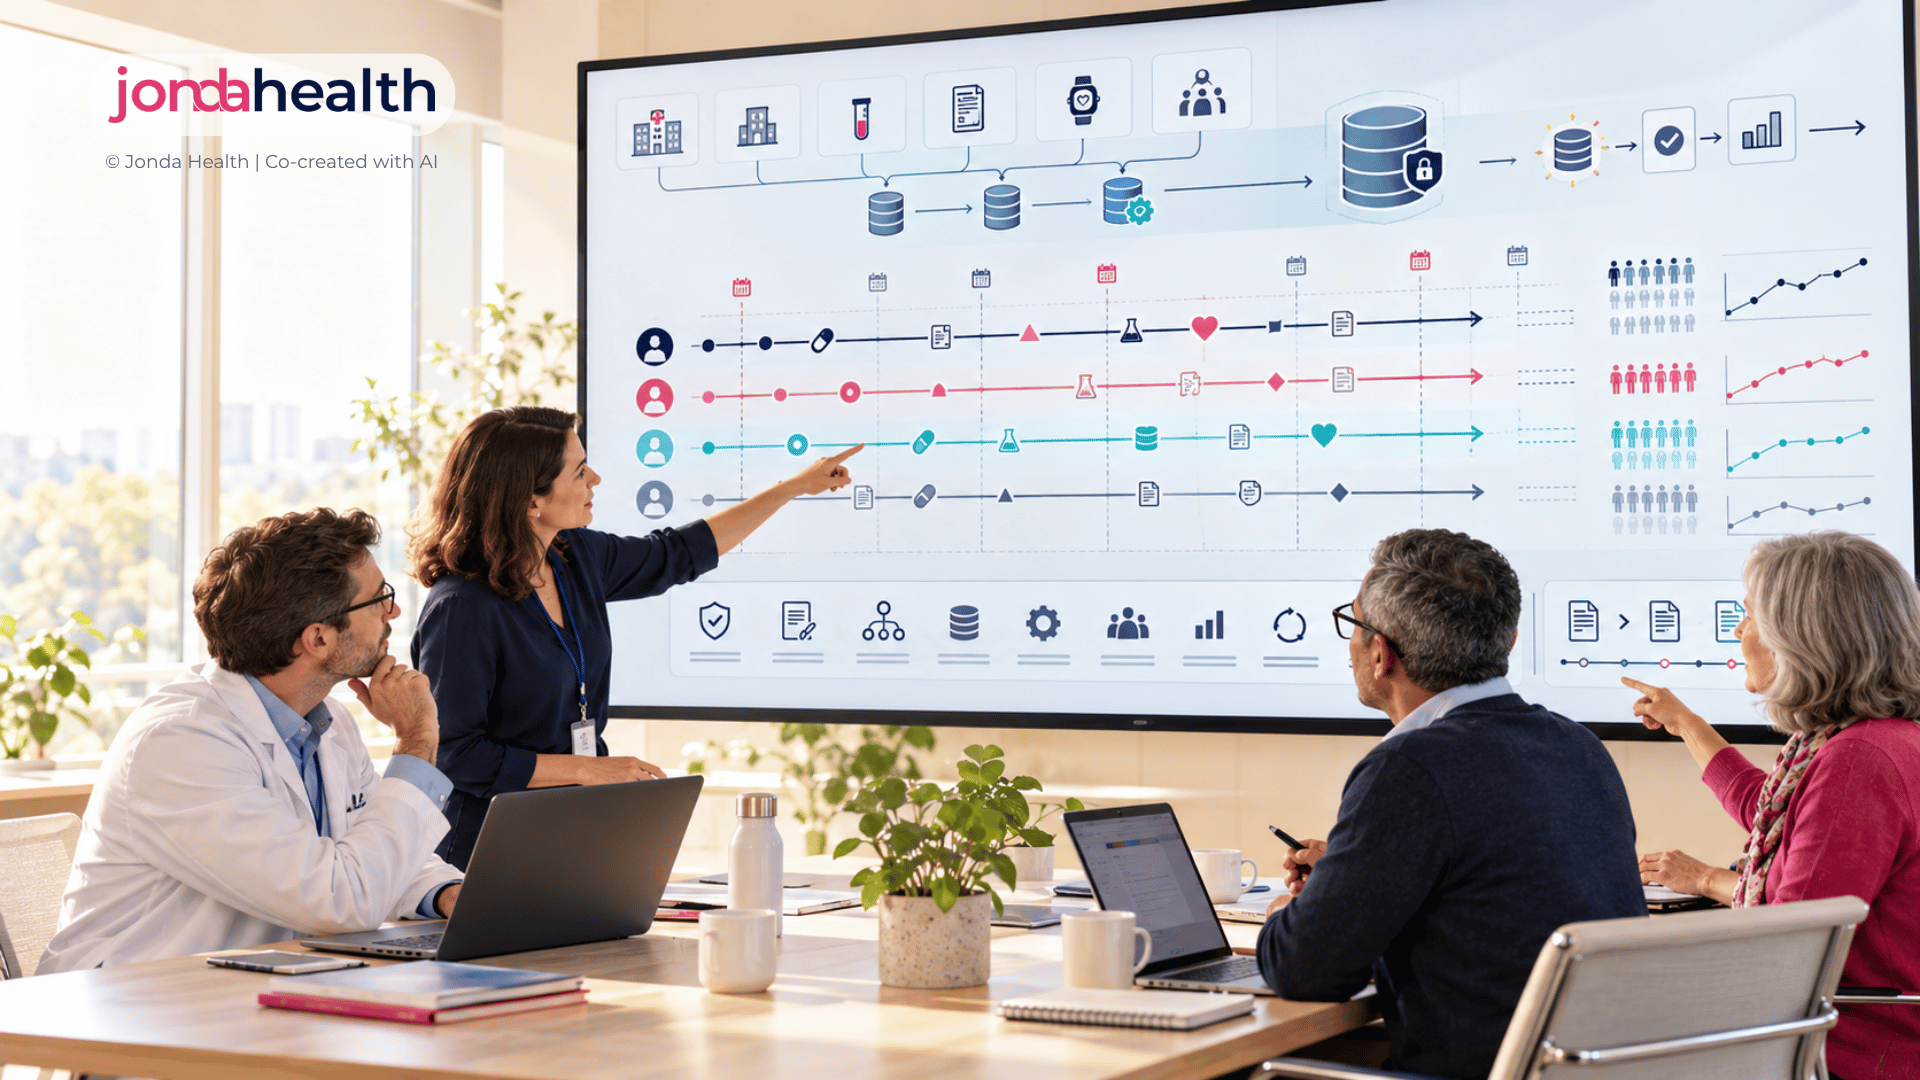
The four stages of a registry. The 12 points below follow this order.
Every later choice, from which fields to collect to how long to follow patients, flows from the purpose of the registry. Write down the handful of questions it must be able to answer in three to five years, and who will ask them. The AHRQ user's guide treats defining goals and objectives as the first step in planning, including asking honestly whether a registry is the right tool at all.1
If there is any chance the data will one day support a regulatory decision, say so now. Regulators assess whether registry data is fit for a specific use, and the FDA places responsibility on sponsors to ensure a registry supports relevant and reliable data, even when the registry is run by another organisation.3 That is far easier to build in than to retrofit.
Tip: If the stakeholders cannot agree on three priority questions, pause the build. That disagreement will not get smaller once data starts arriving.
Every field added to a registry is a small cost paid by someone at every visit, for every patient, for years. A short, well-defined core that sites complete reliably is worth more than an ambitious form that is half empty. Additional disease-specific or study-specific modules can sit on top of the core for the sites and periods that need them.
You do not have to start from a blank page. In rare diseases, the European Platform on Rare Disease Registration published a set of 16 common data elements that every rare disease registry is encouraged to collect, covering personal data, diagnosis, disease history and care pathway, research and disability.4 AHRQ's guidance also points registries towards common data elements and standardised outcome measures.1 Aligning with an existing core makes it far easier to pool data with other registries later.
Pitfall: Adding fields "while we are at it" at each committee meeting. Keep a change log and ask who will use each new field, and for which question.
A data dictionary defines every field: its meaning, format, unit, allowed values, and when it should be recorded. Without one, "date of diagnosis" can mean the date of first symptoms at one site, the date of a confirmatory test at another, and the date the patient was first seen in clinic at a third. All three are reasonable, and together they make analysis unreliable.
The dictionary is also where you record which medical coding standards the registry uses for diagnoses, tests and medications, and where you note any local code sets that participating institutions maintain and how those will be handled.
Registries outlive their founding teams and their first funders. Consent and governance should anticipate secondary research, sharing with academic and industry partners, linkage to other data sources, and what happens if the registry is transferred to another organisation. AHRQ added a dedicated chapter on governance to its fourth edition, including how to engage patient representatives throughout the registry's life.1
Patient organisations have a particular strength here. Governance that patients helped shape tends to earn more trust and more participation, which directly affects how long a registry lasts.
Almost every patient enrolled in a registry arrives with a history: years of laboratory reports, imaging results, referral letters, discharge summaries and medication lists, often from several institutions and sometimes in several languages. In rare diseases this history can stretch across a long diagnostic journey and several countries. It is frequently the most valuable data the registry will ever hold, because it describes what happened before anyone was paying close attention.
Decide early how much of that history to capture, how far back to go, and who will do it. Manual abstraction by research staff is slow, expensive and hard to sustain beyond a pilot. Planning backfill as a proper workstream, with its own quality checks, avoids a registry that only ever describes patients from the day it launched.
The gap between what arrives and what a registry can use is where most of the effort, and most of the stalling, happens.
The most common reason a registry declines is that contributing costs sites more than it gives back. Double entry, where a clinician documents care in the clinical system and then types the same information into a registry form, is a slow drain on goodwill. AHRQ's fourth edition places particular emphasis on how registries can reuse existing data sources, including electronic health records, rather than collecting everything afresh.1
Wherever possible, let sites send what they already have, in the format they already have it, and do the structuring centrally. Then give something back: site-level summaries, benchmarking against peers, or data that helps them run their own clinic. A registry that is useful to its contributors is one they keep feeding.
Tip: Time how long it takes a site to submit one patient's follow-up. If it is more than a few minutes of clinician time, that number will decide your registry's future more than any policy will.
A registry that spans several sites, or several countries, will receive the same result in different units, the same diagnosis under different local codes, and clinical notes in different languages. This is especially true across Asia and Africa, where a single registry may draw on public hospitals, private laboratories and specialist centres with very different systems.
Deal with this as a designed process rather than a clean-up task. Convert units with the original value preserved, map local codes to the registry's chosen standards while keeping a record of the source code, and treat translated content with the same review as any other clinical data. The EMA notes that differences in data types, structures and processing between registries are a common obstacle when assessing whether a registry is suitable for a study.2
The value of a registry is the patient journey over time: how the condition progressed, which treatments were tried, what happened next. That depends on reliably recognising the same person across visits, sites and years, without exposing who they are. Agree how patients will be identified and pseudonymised at the start, including how duplicate enrolments at two centres will be detected and resolved.
Linkage decisions are very hard to reverse. A registry that cannot confidently join a patient's 2024 record to their 2027 record has lost most of what made it worth building.
Automated checks are essential and catch a great deal: missing fields, impossible dates, values outside plausible ranges. What they miss are values that look plausible but are clinically wrong, such as a result attached to the wrong test, a unit silently mislabelled, or a medication recorded at a dose that makes no sense for the patient's age. Catching those needs clinically trained reviewers who understand the condition.
Build review into the workflow with clear rules on what is checked, by whom, and how corrections are recorded. The EMA guideline highlights data quality management as one of the core areas for registry-based studies,2 and a documented review process is part of what lets others trust your data.
Many countries now set clear expectations on where health data may be processed and who may access it. Before choosing tools or partners, confirm what local law requires for processing, storage, transfer and access, and whether data must stay in country. Registries that span borders need an answer for each participating country.
Pseudonymise as early in the pipeline as possible, keep identifiable data separated and tightly controlled, and make sure any partner processing data on the registry's behalf can do so within the required jurisdiction.
Missing follow-up is one of the quiet ways a registry loses value. Patients move, change clinics or simply stop attending, and sites lose the staff member who championed the registry. In its final guidance, the FDA added text asking registries to have a plan for missing assessments, including outreach to patients who lose contact, for example through text messages, phone calls, emails or help with transport.3
The same thinking applies to sites. Track contribution rates by site, notice early when one starts to slip, and find out why before it stops altogether.
Even if publication or regulatory use feels distant, the foundations need to be laid now. That means keeping metadata about how and when each value was captured, an audit trail of every change, version-controlled data dictionaries, and documentation of your quality processes. The FDA's final guidance notes that sponsors using registry data should have access to the metadata associated with it.3 The EMA guideline includes an annex on good practice in establishing and managing registries for regulatory purposes.2
A registry that can show how its data was produced can answer far more questions, for far more people, than one that simply holds the data.
If two or more of these are a "not yet", that is the place to start.
Registries sit exactly where we spend our time: in the layer between the records people already have and the structured, standardised information that clinicians, researchers and systems can actually use. We support registries in two ways, and many teams use both.





