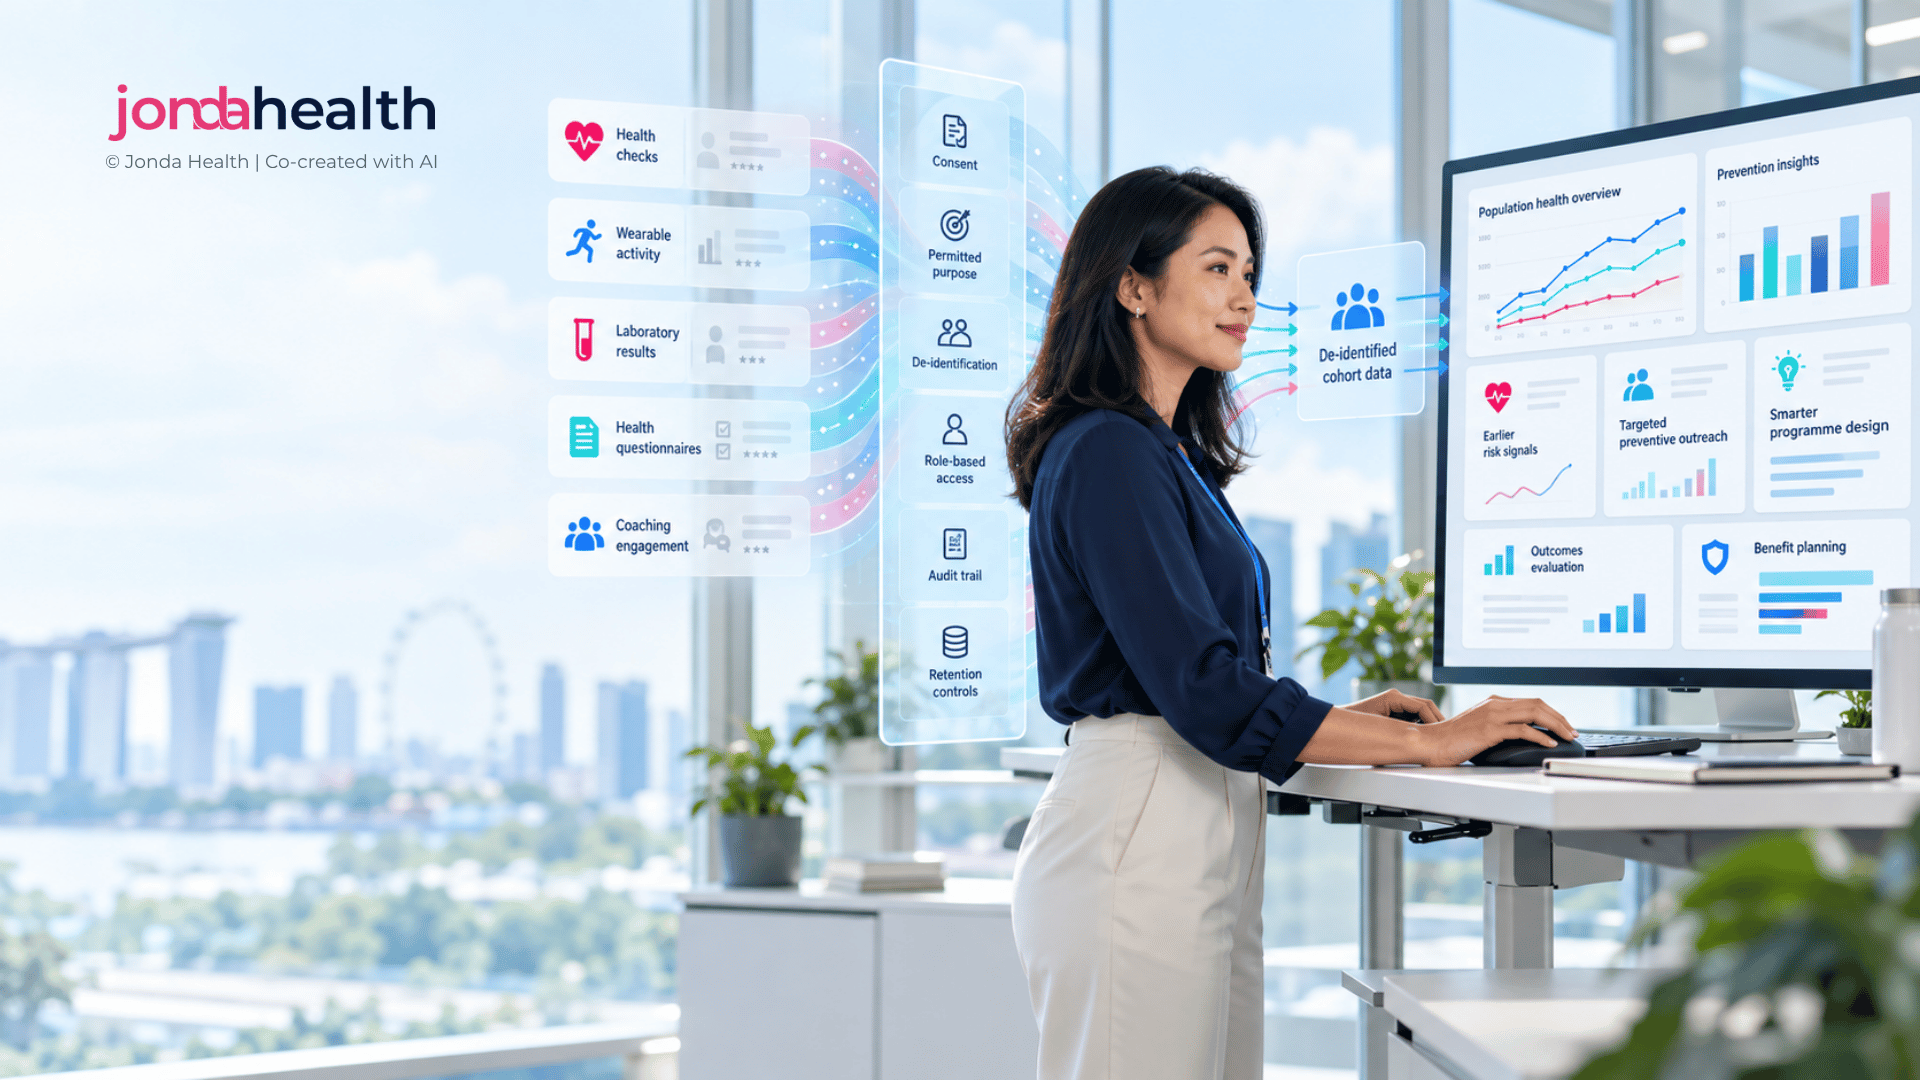
Health checks, device readings and questionnaires tell an insurer more about its members' health than almost anything else it holds. Here are five ways to put that data to work for members, and the guardrails that keep it trustworthy.

Wellness programme data, such as health check results, home device readings and health risk questionnaires, shows an insurer what its members' health looks like before they need care. Used within clear rules, it supports early outreach, care navigation, targeted coaching, programme design and evaluation.
Most insurers know a great deal about what happened to their members after they became unwell. Claims data shows the hospital stays, the procedures and the medicines. What it rarely shows is the period before, when a blood sugar result was creeping up, a blood pressure reading was borderline, or a doctor wrote "repeat test in three months" on a health check report.
That earlier picture is exactly what a wellness programme collects. Members share it voluntarily, often every year, in return for support and rewards. Used well, it gives an insurer the chance to help members while they are still well, which is better for them and aims to reduce the need for more serious care later.
Used carelessly, the same data can damage trust very quickly. Members who suspect their wellness data might affect their cover will stop sharing it, and regulators in most markets expect personal data to be used only for the purposes people agreed to.1,2 This guide is written for chief medical officers, health management and wellness leads, and product and data teams inside insurers. It sets out five ways to use wellness data for prevention, and the guardrails that let you do it with confidence.
Figure 1. Claims data starts when care begins. Wellness data shows the years before, where prevention can still change the course.
The most valuable moment is before anything has happened.
The clearest use of wellness data is spotting members whose results suggest rising risk and reaching out while there is still time to act. That might be a member whose fasting glucose has risen two years in a row, whose home blood pressure readings have crept up since their last check, or whose doctor recommended a repeat test that never appeared in the programme.
The outreach itself should feel like support, not surveillance: a nurse call, a personal message in the app, an invitation to a coaching programme, or a reminder to rebook a test. The member should understand why they are being contacted and that it is part of the wellness programme they joined.
The data it depends on: Results captured in full, including recommendations written in doctor's summaries, made comparable across providers and years so that a rise is real and not an artefact of different units or labs, and linked reliably to the right member.
A finding is only useful if the member knows where to take it.
Members often do not know what to do with a result. Should a mildly abnormal value go to their general practitioner, a specialist, or simply be repeated in a few months? Should an imaging finding be reviewed urgently, or at the next routine visit? Without guidance, some members ignore findings that matter, while others go straight to expensive specialist care they may not need.
Wellness data lets an insurer offer care navigation that is specific to the member's own results: suggesting the right type of follow-up, pointing to suitable providers in the network, and helping the member understand what the finding means in plain language.
The data it depends on: Findings captured with enough clinical detail to judge what level of follow-up is appropriate, and reviewed by clinically trained people where the meaning is uncertain, so that guidance is never based on a misread value.
Support spread evenly is support spread thin.
Coaching, nurse support and condition programmes cost money, and most insurers cannot offer intensive support to every member. Without data, these resources tend to go to the members who ask for them, who are often already motivated and relatively healthy. With good wellness data, an insurer can invite the members most likely to benefit, such as those with several borderline results, or those whose questionnaire answers suggest stress and poor sleep alongside rising blood pressure.
Figure 2. Good data lets support follow need.
The data it depends on: Clinical results, device readings and questionnaire answers linked to the same member and held in a consistent structure, so that rules for inviting members can draw on more than one source.
What is common across your members should shape what you offer them.
Looked at in aggregate, wellness data shows patterns that no single member's record can. One client's workforce may have unusually high blood pressure risk; members in one market may be skipping a particular screening; younger members may engage well with the app but rarely complete a health check. These patterns can shape new condition programmes, the screenings included in a health check package, the design of rewards, and the benefits offered to corporate clients.
The data it depends on: Consistent definitions across all members, clients and markets, so that patterns reflect real differences in health and not differences in how data was captured. Pseudonymised, aggregated data is usually all this needs.
Every intervention is an experiment worth learning from.
Insurers run many prevention initiatives: reminders, coaching, challenges, screening campaigns, condition programmes. Few can say with confidence which of them changed anything. Wellness data, collected consistently over time, makes it possible to compare members who took part in an initiative with similar members who did not, and to see whether results moved in the right direction.
This evidence matters inside the insurer, where it guides where to invest next, and outside it, where corporate clients increasingly ask what the programme achieved. Our guide The Renewal Question covers the questions clients ask at renewal in more detail.
The data it depends on: Comparable measures across years and providers, a record of who received which intervention and when, and enough follow-up results to see change, all captured from the start of the programme rather than assembled afterwards.
Trust is the condition for everything above.
Every use in this guide depends on members continuing to share their data. That depends on trust, and trust depends on members seeing that their wellness data is used to support them and not against them. A simple way to frame decisions is to sort proposed uses into three groups before anyone builds anything.
Figure 3. A simple way to sort proposed uses before anyone builds them. Where each use falls depends on your markets and on what members agreed to.
Behind this sorting sit a few practical habits. Tag every data point with where it came from and what it may be used for. Pseudonymise data before it reaches analysis and reporting. Report to employers only in aggregate, with small groups hidden. Keep the teams and systems that support members separate from those that make cover and pricing decisions. And tell members, in plain language inside the app, exactly how their data is and is not used.
Within the purpose members agreed to, insurers can use wellness data to reach members early when risk is rising, guide them to the right care, direct coaching to those who need it most, design better programmes from aggregate insight, and measure which initiatives work.
Only where members have clearly agreed and local law allows it. In most markets, personal data must be used for the purposes people were told about, so many insurers keep wellness data separate from individual cover, pricing and claims decisions. Take advice for each market.
Pseudonymised data has direct identifiers replaced, so it can still be linked back to a person under controlled conditions and is still personal data. Anonymised data cannot reasonably be linked to anyone. Most programme analysis uses pseudonymised data with strict controls.
Structured health check results show what a member's findings mean and what level of follow-up suits them, so an insurer can suggest the right type of care, point to suitable providers, and explain results in plain language, with clinical review where meaning is uncertain.
Capture comparable measures from the start, record who received each intervention and when, and compare change among participants with similar members who did not take part, using pseudonymised data and clear notes on what the data can support.
JondaX turns health check documents and photographed device readings into structured, consistent data configured to an insurer's measures, with clinical review of flagged values, pseudonymisation and in-country processing where required, so prevention rules can run on trusted data.
Jonda Health helps insurers and their wellness partners make wellness data usable for prevention, with privacy built into how it flows rather than added afterwards.
About the author. Suhina Singh is Founder & CEO of Jonda Health. She has spent her career in healthcare, first as a doctor working in oncology, then in medical affairs and digital transformation roles across Asian markets, and as an investor in and builder of digital health products. She founded Jonda Health in 2021 to make health data usable for the people and systems that depend on it.
This guide offers general information, not legal advice. Data protection and insurance rules vary by market, and insurers should seek advice for the markets they operate in.





