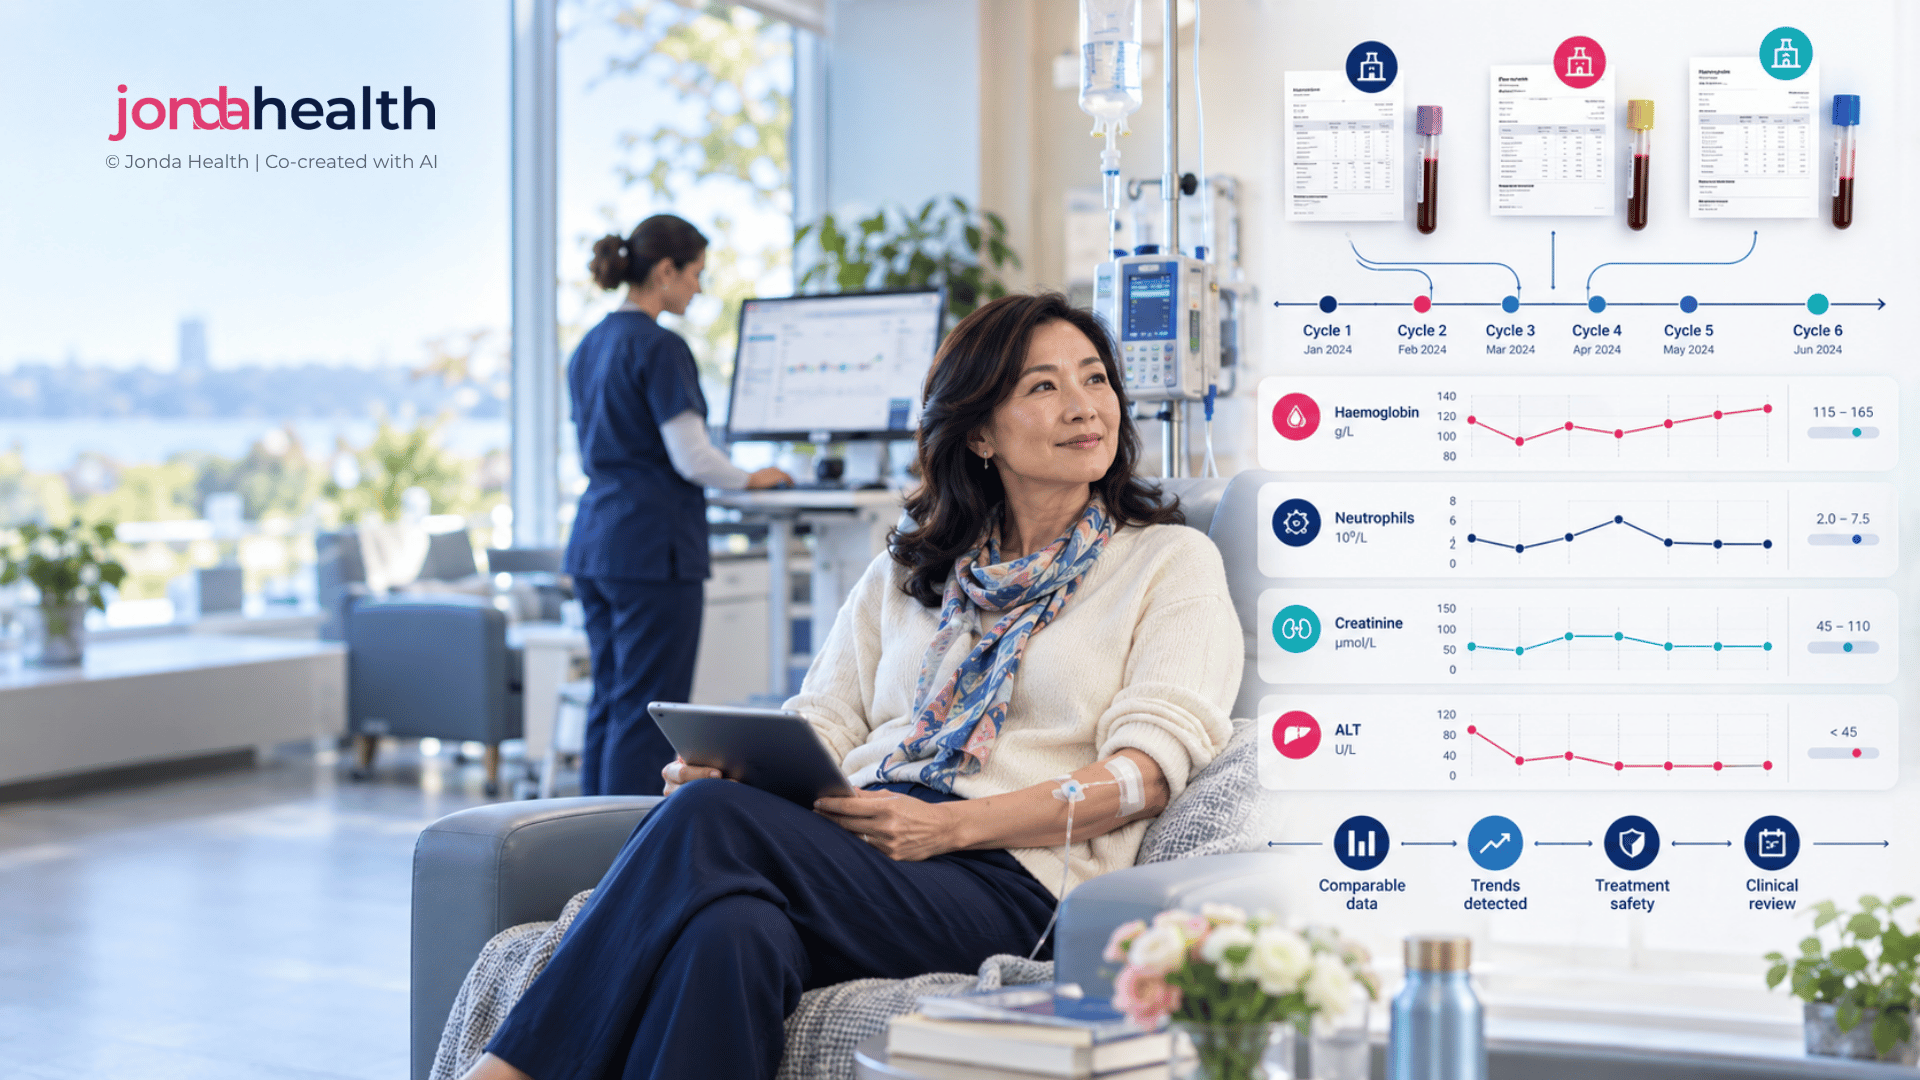
Tracking Cancer Treatment Through Labs: 9 Reasons Oncology Needs Harmonised Lab Data
Laboratory results collected before, during and after therapy are central to assessing treatment response. This guide looks at where that evidence becomes fragmented across reports, laboratories and clinical notes, and how harmonisation restores a complete, analysis-ready patient record.
Mugdha Raut
Team Lead - Quality Assurance
October 2, 2026
·
9 min read
Key takeaways
Oncology lab results only become meaningful as a timeline: at baseline, before each cycle, and at intervals after treatment.1
Response and progression rules for tumour markers such as cancer antigen 125 (CA-125) and prostate-specific antigen (PSA) are defined by change from a baseline or nadir.2, 3
Results from different assays, units and test names cannot be compared directly until they are harmonised.7, 8, 12
Clinical text holds information that structured records miss,9 including lab values quoted in physician notes. Leaving notes out leaves gaps in the patient record.
In oncology, nearly every critical decision is informed by laboratory results, and those results only carry meaning when they can be read in sequence. A single value rarely settles anything. The question is almost always how today's number compares with the one before it, and with the baseline taken before treatment began.
Oncology lab data harmonisation is the process of turning lab results from different reports, laboratories and clinical notes into one consistent, reviewed record. Each value is extracted with its date, unit and source; the many ways the same test is named and captured are resolved; units are normalised; results are checked clinically; and each test is mapped to medical coding standards or to an institution's own code set. The result is a patient record that can be trended and analysed as a whole.
Where labs sit in the treatment journey
Stage 1
Before treatment
Baseline counts, organ function and tumour markers
01
Stage 2
Each cycle
Go or delay checks, plus immune-related monitoring
0208
Stage 3
Response checks
Marker trends read against formal criteria
0304
Stage 4
After treatment
Surveillance for recurrence, then research use
0309
At every stage: different labs and assays 05 different test names 06 values held in notes 07
1. Baseline labs set the reference point for everything that follows
Before a regimen begins, a full blood count, liver and kidney function tests and relevant tumour markers establish whether the patient can tolerate treatment. They also define the reference point for every later comparison. Some doses are calculated directly from these values: carboplatin, for example, is commonly dosed from kidney function using the Calvert formula, where the dose equals the target area under the curve multiplied by the glomerular filtration rate plus 25.5
Where the baseline is missing, or held only in a scanned referral letter, every later assessment of change is compromised.
With JondaX: baseline values are extracted from whichever report or letter holds them and fixed as the first point on the patient's timeline.
2. Pre-cycle checks decide whether the next dose goes ahead
Before each cycle, neutrophils, platelets, haemoglobin, liver enzymes and creatinine are reviewed to decide whether treatment proceeds on schedule, is deferred, or needs a dose change. Adverse events, including abnormal lab values, are graded with the US National Cancer Institute's (NCI) Common Terminology Criteria for Adverse Events (CTCAE), the standard for assessing and reporting adverse events in cancer trials. CTCAE v6.0 was released in 2025.6
IllustrativePlatelets across four cycles, from four documents
Platelets (×109/L). Dashed line: lower limit of normal (150). Seen together, the downward trend is obvious. Spread across a PDF, a scan and a clinic note, it is easy to miss.
With JondaX: pre-cycle results line up by date, so cycle-on-cycle changes are visible at a glance.
3. Tumour markers are interpreted as trends, not single values
The NCI notes that serial measurements of a tumour marker during treatment can indicate whether the tumour is responding, and that periodic measurement after treatment may be used to check for recurrence.1 Common examples include PSA, CA-125, carcinoembryonic antigen (CEA), alpha-fetoprotein (AFP) and beta human chorionic gonadotrophin (beta-hCG).
An isolated CA-125 of 70 U/mL offers limited insight. A CA-125 that fell from 800 U/mL to 40 U/mL and is now rising carries clear clinical significance.
IllustrativeOne CA-125 series, read as a trend
CA-125 (U/mL) on a logarithmic scale; C = cycle. The nadir of 40 never falls below the upper limit of normal (35 in this example). Under GCIG criteria, two values at or above twice the nadir, at least one week apart, indicate progression.12
With JondaX: every marker value, from every source, is placed on one longitudinal series ready to trend.
4. Response and progression rules depend on precise, dated values
Formal response criteria measure change from a defined reference point. A missing collection date or a single transcription error can change the classification.
Rule box · Criteria in use
Ovarian cancer (Gynecologic Cancer InterGroup, GCIG, CA-125 criteria): response is at least a 50% reduction from a pre-treatment sample, confirmed and maintained for at least 28 days; the pre-treatment value must be at least twice the upper limit of normal and taken within two weeks before treatment. Progression is a CA-125 of at least twice the upper limit of normal (or twice the nadir, if it never normalised) on two occasions at least one week apart.2, 12
Prostate cancer (Prostate Cancer Clinical Trials Working Group 3, PCWG3, used in castration-resistant prostate cancer trials): after a decline, progression is an increase of at least 25% and at least 2 ng/mL above the nadir, confirmed by a second PSA measurement three or more weeks later. Early rises in the first 12 weeks are ignored.3
Solid tumours (Response Evaluation Criteria in Solid Tumours, RECIST 1.1): the imaging standard for response. Tumour markers are read alongside it rather than instead of it, and the GCIG advises that tumour measurements take precedence when the two disagree.4, 12
Worked examplePCWG3 PSA progression threshold
PSA nadir4.0 ng/mL
+25% gives5.0 ng/mL
+2 ng/mL gives (both must be met)6.0 ng/mL
A PSA of 5.5 ng/mL meets the 25% rule but not the 2 ng/mL rule, so it is not progression. A value of 6.0 ng/mL or higher, confirmed three or more weeks later, is. Both calculations depend on knowing the true nadir and its date.
With JondaX: values keep their collection date, unit and reference range, so nadirs and percentage changes are calculated from clean data.
5. Different labs, different assays: values are not always interchangeable
Patients are often tested across several sites: the treating cancer centre, local hospitals, community laboratories and trial central laboratories. For tumour markers, this has direct consequences. Mayo Clinic Laboratories states that CA-125 values obtained with different assay methods cannot be used interchangeably,7 and the GCIG criteria require the same assay method to be used for each patient.12 Units also vary from lab to lab.
Same patient, different reports
Haemoglobin12.5 g/dL = 125 g/LSame result, different unit
Creatinine1.0 mg/dL ≈ 88 µmol/LSame result, different unit
CA-125Assay A ≠ Assay BNot interchangeable, even in the same unit
Units can be converted. Assay differences cannot, which is why the method has to travel with every tumour marker value.
Best practice · For analysis
Record the performing lab and method with every tumour marker value. Trend like with like, and flag any switch in lab or assay before interpreting a change.
With JondaX: units are normalised and source metadata is kept with each result, so method changes are visible.
6. The same test goes by many names
"Absolute neutrophil count", "ANC" and "Neutrophils (abs)" are the same measurement under three different labels. Laboratories have historically identified tests with their own internal codes, which is why Logical Observation Identifiers Names and Codes (LOINC) was created: a common set of identifiers and names for health measurements that its maintainers describe as the "global lingua franca" for tests and observations.8
Three labels, one concept
ANCNeutrophils (abs)Absolute neutrophil count
→
Neutrophils, absolute count, bloodMapped to LOINC, or to the institution’s own code set
Mapping is the final part of the work. Before a label can be mapped, the value has to be read correctly, its unit confirmed and any ambiguity resolved, and some institutions maintain their own code sets that need to be honoured alongside the standard.
With JondaX: test names from each lab are resolved and mapped to one concept, in the standard or in the client's own ontology, so every neutrophil count lands in the same column.
7. Some of the most important labs live only in physician and clinical notes
Not every laboratory result is captured in a laboratory report. Outside results, clinician-summarised trends and lab-driven treatment decisions are often documented only in consultation letters, progress notes and tumour board summaries. Illustrative examples:
"CA-125 at the referring hospital was 1,240 in March": potentially the only record of that baseline.
"PSA has risen from 2.1 to 4.8 over three months": a progression signal that never entered the laboratory system.
"Cycle 3 delayed one week, ANC 0.9": a result tied directly to a treatment decision.
A 2025 systematic review in the Journal of the American Medical Informatics Association (JAMIA) found that significant patient information remains locked within clinical text, and oncology was the most common clinical area among the studies it included (six of 15).9 The authors also describe a human-in-the-loop step, in which expert feedback refines what is extracted.
From a sentence in a note to a reviewed data point
Progress note · 14 MayPatient reviewed in clinic. Cycle 3 delayed one week, ANC 0.9. Repeat count before restarting.
→
Test
Absolute neutrophil count
Value
0.9
Unit
×109/L Reviewed
Date
14 May
Source
Progress note, linked
The note gives no unit. A clinically trained reviewer confirms it before the value joins the timeline, and the record keeps a link back to the sentence it came from.
With JondaX: lab values in notes are extracted with test, value, unit and date, checked by clinically trained reviewers when flagged, harmonised to the same standards and linked back to the source note for verification.
8. Immunotherapy adds more labs to watch
Immune checkpoint inhibitors can cause immune-related adverse events affecting the thyroid, liver, endocrine system and kidneys. The American Society of Clinical Oncology (ASCO) guideline on managing these events sets out laboratory monitoring and grading by organ system.10 Such changes can develop gradually and between scheduled visits.
Rule box · ASCO monitoring (2021)
Thyroid: thyroid-stimulating hormone (TSH), with the option of free thyroxine (free T4), can be checked every 4 to 6 weeks as routine monitoring in patients without symptoms.10
Liver: aspartate aminotransferase (AST), alanine aminotransferase (ALT) and bilirubin before each infusion.10
Glucose: at baseline, with each treatment cycle while on therapy, and at follow-up visits for at least six months.10
With JondaX: thyroid, liver, glucose and kidney results from any source sit on the same timeline as the treatment dates.
9. Clean lab data powers trials, registries and real-world evidence
The US Food and Drug Administration (FDA) defines real-world data as data on patient health status or care delivery routinely collected from sources such as electronic health records and registries, and it has had a framework for using real-world evidence in regulatory decisions since 2018.11 Yet assembling a cohort with complete baseline, on-treatment and follow-up laboratory data often still takes months of manual chart abstraction.
With JondaX: structured, harmonised output feeds trial databases, registries and research datasets through a single application programming interface (API), without re-keying.
Not sure where to start? Sometimes the harder question comes before any extraction: whether existing data can support a study at all, how records should flow between sites, or what needs to be pseudonymised and processed in-country. Jonda Health Services works with oncology and research teams on exactly these questions, from assessing health data foundations and planning registry or cohort data flows to designing privacy safeguards, so the data is ready before the analysis begins.
How harmonisation works, step by step
Collect
PDFs, scans, letters, notes and data feeds
Extract
Test, value, unit, date and source
Harmonise
Names, units, ranges and codes
Clinical review
Clinically trained reviewers check flagged values
Deliver
One longitudinal record through a single API
Step 4 is where JondaX differs from extraction alone: flagged values are checked by Jonda Health’s own clinically trained reviewers, giving 99% field-level accuracy with expert review.
Summary: where oncology lab data fragments, and how harmonisation resolves it
Stage
What goes wrong
What harmonisation fixes
Baseline
Value buried in a referral letter or scan
Extracted and fixed as timeline point zero
Before each cycle
Counts spread across separate PDFs
Cycle-on-cycle trends in one view
Response assessment
Mixed assays, units and dates
Normalised values with source and method kept
Clinical notes
Outside and verbal results never structured
Extracted, reviewed, harmonised and linked to the note
Research and real-world evidence
Months of manual abstraction
Analysis-ready structured output
Frequently asked questions
What is oncology lab data harmonisation?
It is the process of turning lab results from different reports, laboratories and clinical notes into one consistent, reviewed record. Each value is extracted with its date, unit and source, variant test names and captures are resolved, units are normalised, results are checked clinically, and each test is mapped to medical coding standards or to an institution's own code set, so a patient's results can be trended and analysed together.
Why do tumour markers need to be tracked as a trend?
A single value has limited meaning. Serial measurements during and after treatment show whether a tumour is responding or recurring,1 and criteria such as the GCIG CA-125 and PCWG3 PSA definitions are based on change from a baseline or nadir.2, 3
Can lab results in physician notes be extracted?
Yes. Values quoted in physician and clinical notes, such as outside results or trends summarised by the oncologist, can be extracted with test name, value, unit and date, checked by a clinically trained reviewer where needed, harmonised, and placed on the same timeline as lab reports, with a link back to the source note.
Who benefits most from harmonised oncology lab data?
Oncology practices receiving results from many labs, clinical research teams and contract research organisations (CROs) running oncology trials, real-world evidence and outcomes researchers, and health networks running registries or quality programmes.
How does JondaX help oncology teams?
JondaX is a real-time health data transformation engine: any format in, clean structured output out, through a single API. It extracts lab results from PDFs, scanned reports and clinical notes, harmonises them with review by clinically trained staff, and delivers them for clinical review, trials and real-world evidence. Jonda Health is ISO 27001 certified, JondaX is designed to comply with the Health Insurance Portability and Accountability Act (HIPAA), the General Data Protection Regulation (GDPR) and Singapore's Personal Data Protection Act (PDPA), and processing can take place in-country. Read more in Reading a Lab Report with AI Is Not the Same as Making It Usable.
Assess your oncology data with JondaX
Share a pseudonymised sample of oncology lab reports and clinical notes, and our team will show you extraction, clinical review and harmonisation into a single, longitudinal patient record.
National Cancer Institute. Tumor Markers (fact sheet). cancer.gov.
Rustin GJ, Vergote I, Eisenhauer E, et al. Definitions for response and progression in ovarian cancer clinical trials incorporating RECIST 1.1 and CA 125 agreed by the Gynecological Cancer Intergroup (GCIG). Int J Gynecol Cancer. 2011;21(2):419-423. PubMed 21270624
Scher HI, Morris MJ, Stadler WM, et al. Trial design and objectives for castration-resistant prostate cancer: updated recommendations from the Prostate Cancer Clinical Trials Working Group 3. J Clin Oncol. 2016;34(12):1402-1418. PMC4872347
Eisenhauer EA, Therasse P, Bogaerts J, et al. New response evaluation criteria in solid tumours: revised RECIST guideline (version 1.1). Eur J Cancer. 2009;45(2):228-247. doi:10.1016/j.ejca.2008.10.026
Calvert AH, Newell DR, Gumbrell LA, et al. Carboplatin dosage: prospective evaluation of a simple formula based on renal function. J Clin Oncol. 1989;7(11):1748-1756. ascopubs.org.
Liu L, Blake V, Barman M, et al. Using natural language processing to extract information from clinical text in electronic medical records for populating clinical registries: a systematic review. J Am Med Inform Assoc. 2026;33(2):484-499. Published online 15 October 2025. doi:10.1093/jamia/ocaf176
Schneider BJ, Naidoo J, Santomasso BD, et al. Management of immune-related adverse events in patients treated with immune checkpoint inhibitor therapy: ASCO guideline update. J Clin Oncol. 2021;39(36):4073-4126. doi:10.1200/JCO.21.01440
This article is for information only and does not replace clinical guidelines or professional judgement. Charts and note excerpts are illustrative examples, not patient data.